

Main decision tree
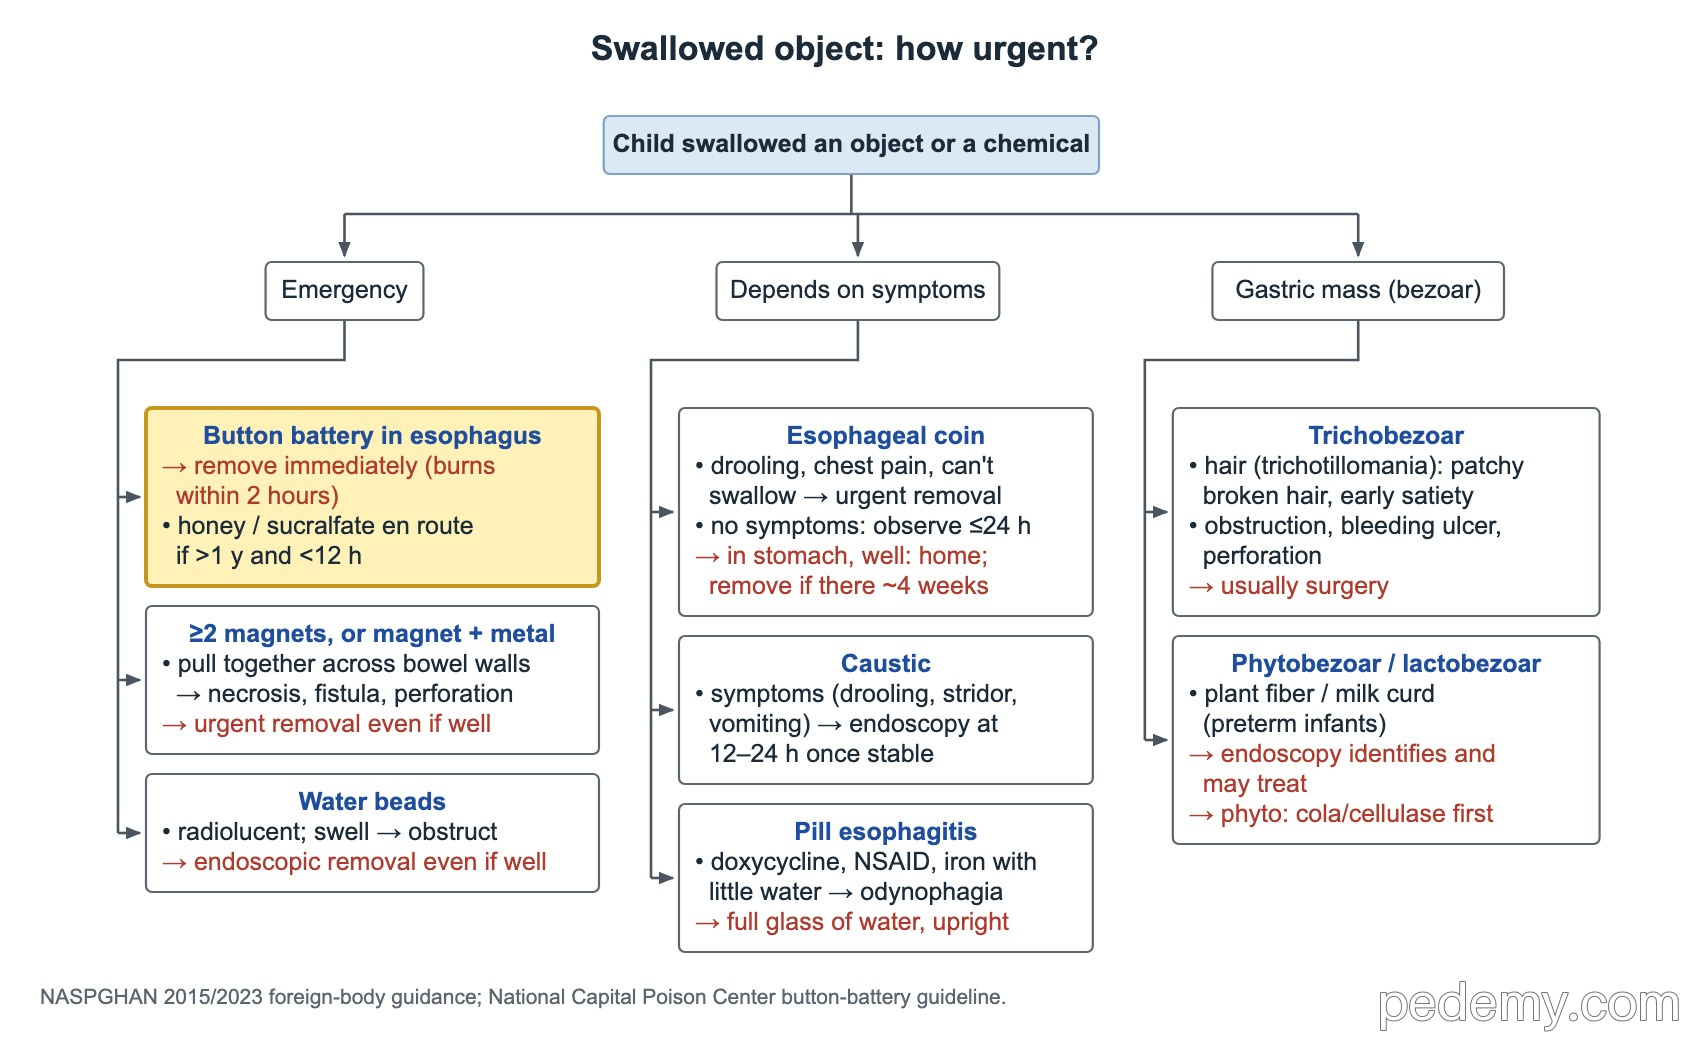
Swallowed object: how urgent?
Key points
- Button battery in the esophagus: remove immediately, ideally within 2 hours; honey or sucralfate on the way if age >1 year and <12 hours since ingestion.
- Two or more magnets, or a magnet plus metal: urgent removal even if the child is well.
- Water beads are radiolucent and swell: urgent endoscopic removal even if well.
- Asymptomatic esophageal coin: observe up to 24 hours with a repeat X-ray; still there at 24 hours → endoscopic removal.
- Symptomatic caustic ingestion: endoscopy at 12–24 hours once stable.
- Eosinophilic esophagitis: ≥15 eosinophils per high-power field on biopsy; treat with PPI, swallowed steroid, diet or dupilumab.
- Achalasia: confirm with high-resolution manometry; myotomy (POEM or Heller) gives the best long-term result.
Emergencies: button batteries, magnets and water beads
Start with AP and lateral X-rays of the neck, chest and abdomen for any suspected swallowed object. A button battery shows a double ring (halo) on AP view and a step-off on lateral view.
A button battery in the esophagus is removed at once: it causes burns within 2 hours. Do not wait for fasting time or symptoms. If the child is over 1 year and ingestion was within 12 hours, give honey or sucralfate on the way, without delaying removal.
- Never induce vomiting (ipecac): it risks aspiration and more esophageal injury.
- Objects longer than 5 cm or sharp objects: urgent endoscopic removal.
- Late diagnosis of an esophageal battery (more than 12 hours): CT for vascular injury before removal is suggested.
Magnets and water beads
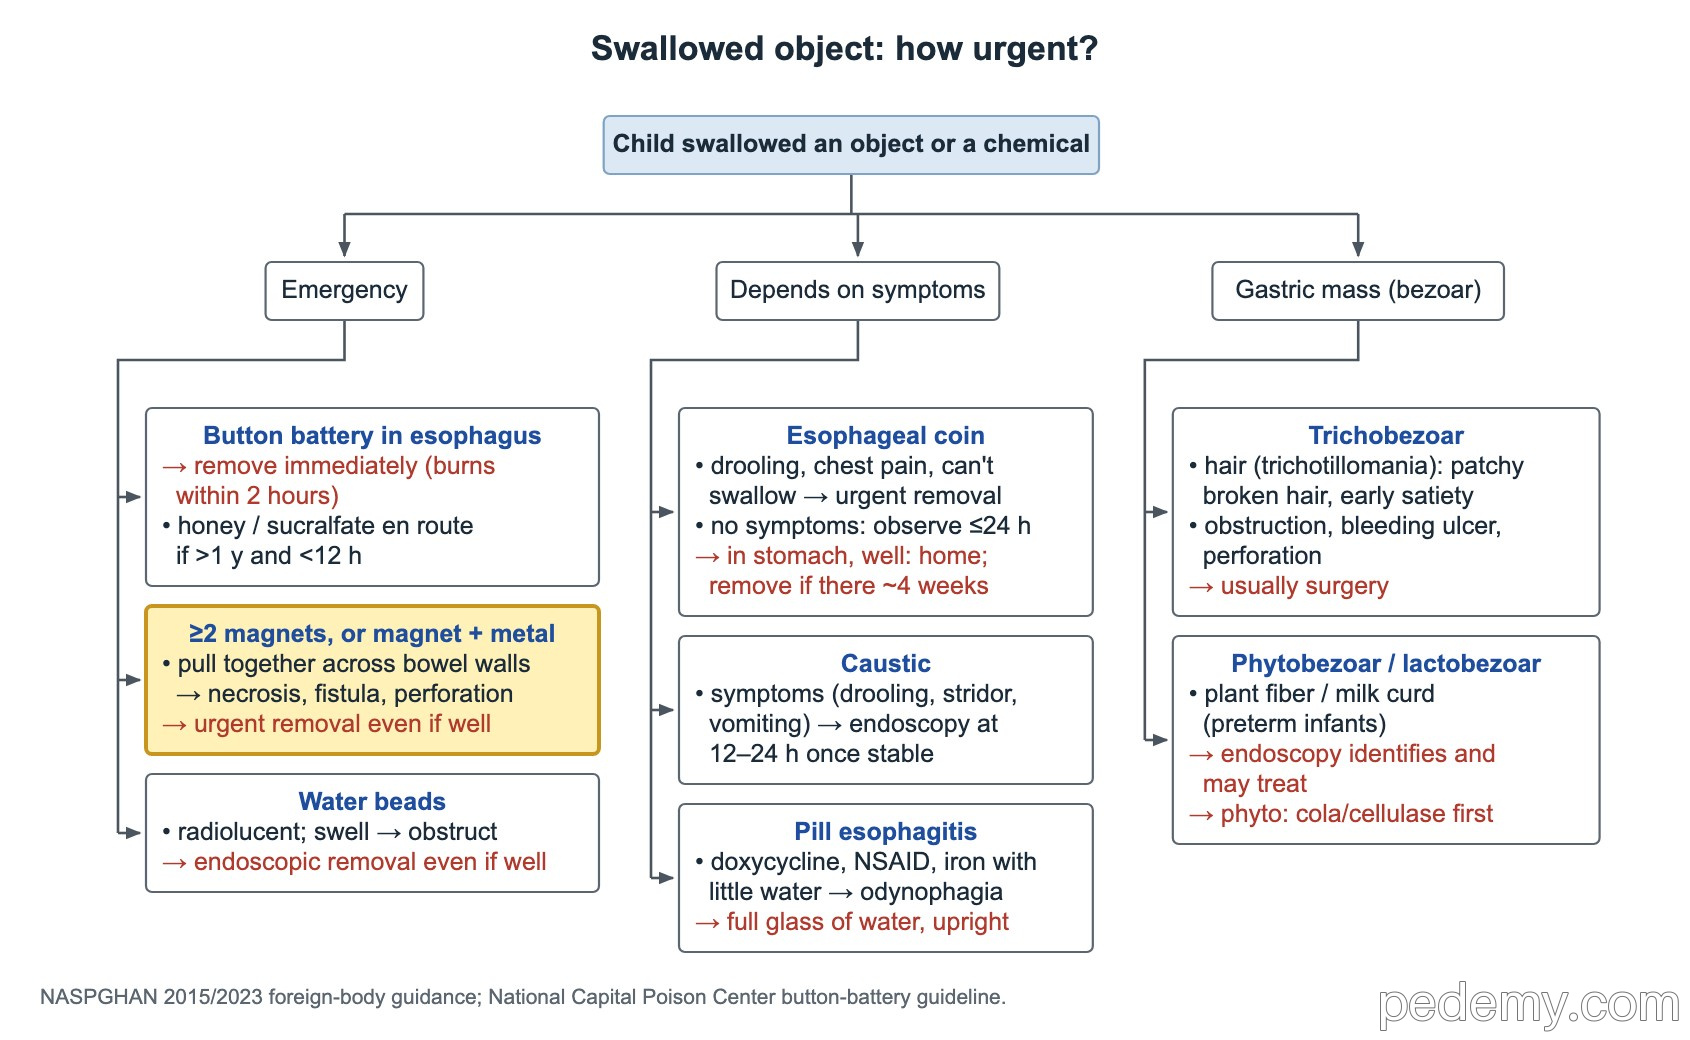
- Two or more magnets, or a magnet plus a metal object, attract each other across bowel walls. This causes pressure necrosis, fistula or perforation, even in a child with no symptoms, so remove them urgently.
- Water beads (superabsorbent polymer) are usually invisible on X-ray and swell in the intestine, causing small bowel obstruction.
- Water beads, even in a well child seen soon after ingestion: urgent endoscopic retrieval while they are still in reach.
- Water beads with obstruction signs: emergency endoscopic removal and a surgical consult.
Coins
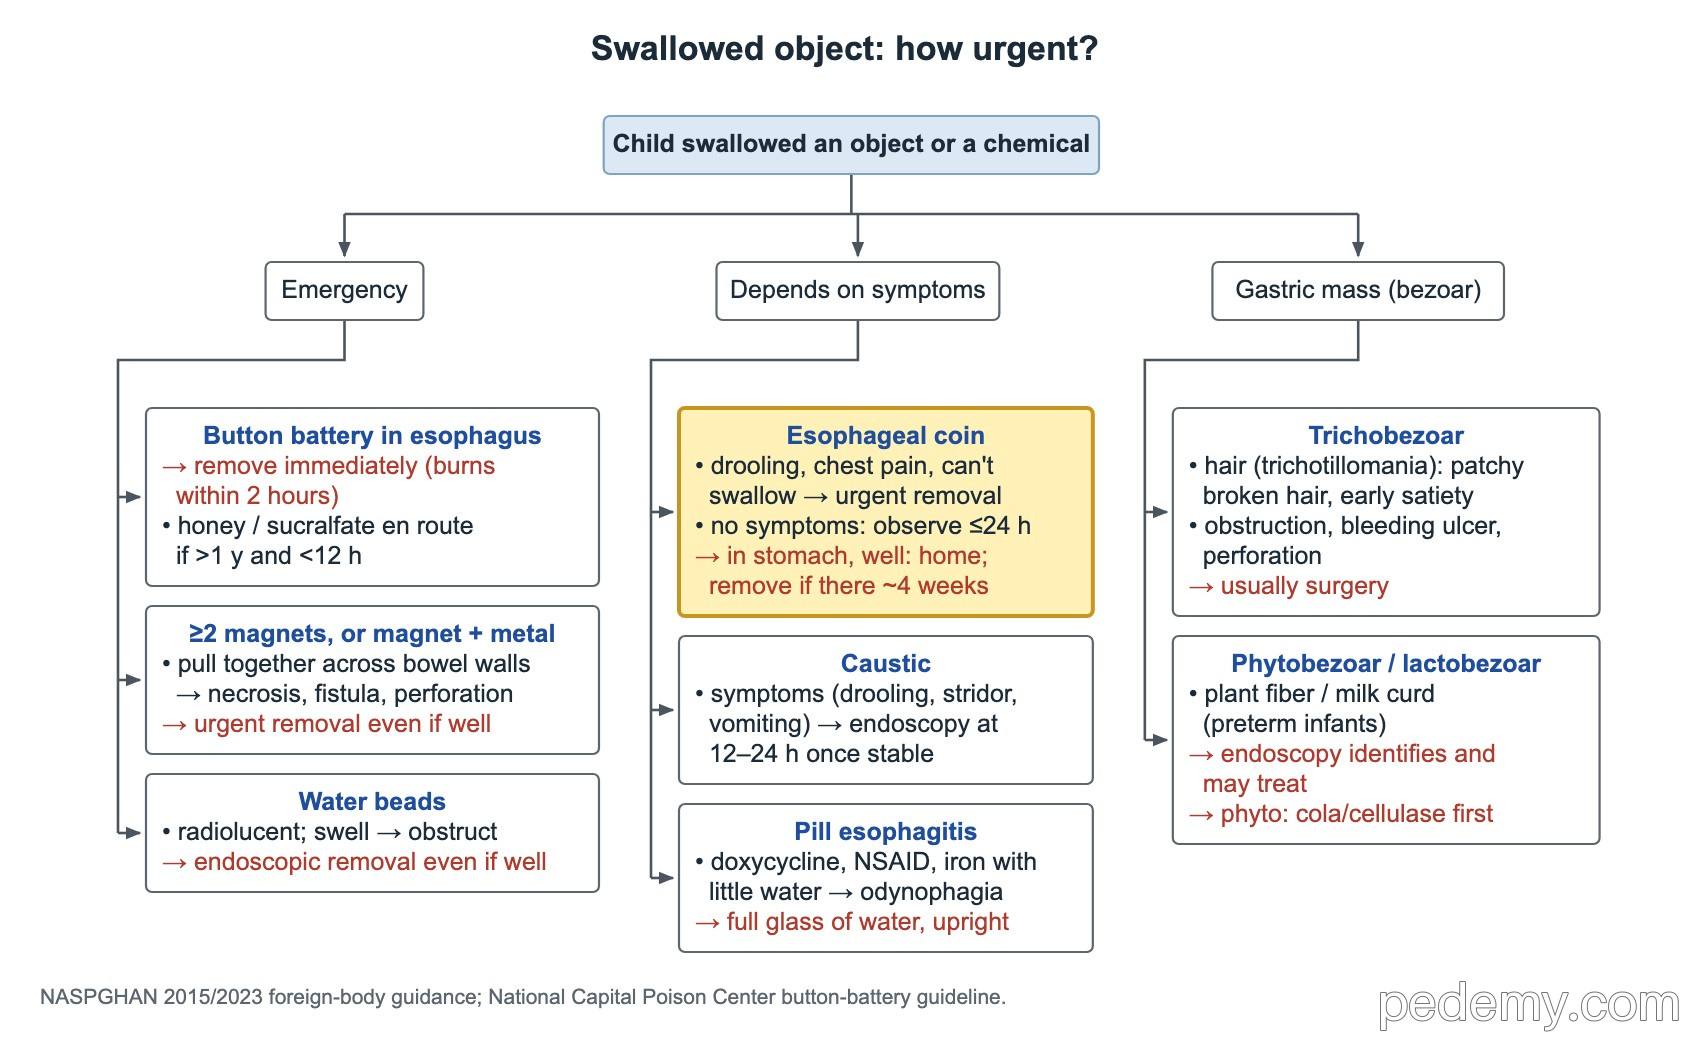
Coins are the most common object children swallow. In the esophagus they usually lodge at the upper esophageal sphincter (cricopharyngeus).
- Drooling, chest pain or inability to swallow: urgent removal.
- No symptoms: observe up to 24 hours and repeat the X-ray at 12–24 hours; many pass into the stomach.
- Still in the esophagus at 24 hours, or time of ingestion unknown: endoscopic removal.
- A coin left too long can cause stricture, perforation, or aortoesophageal or tracheoesophageal fistula.
- Coin in the stomach, child well: home, normal diet; remove if still there after about 4 weeks.
Caustics and pill esophagitis
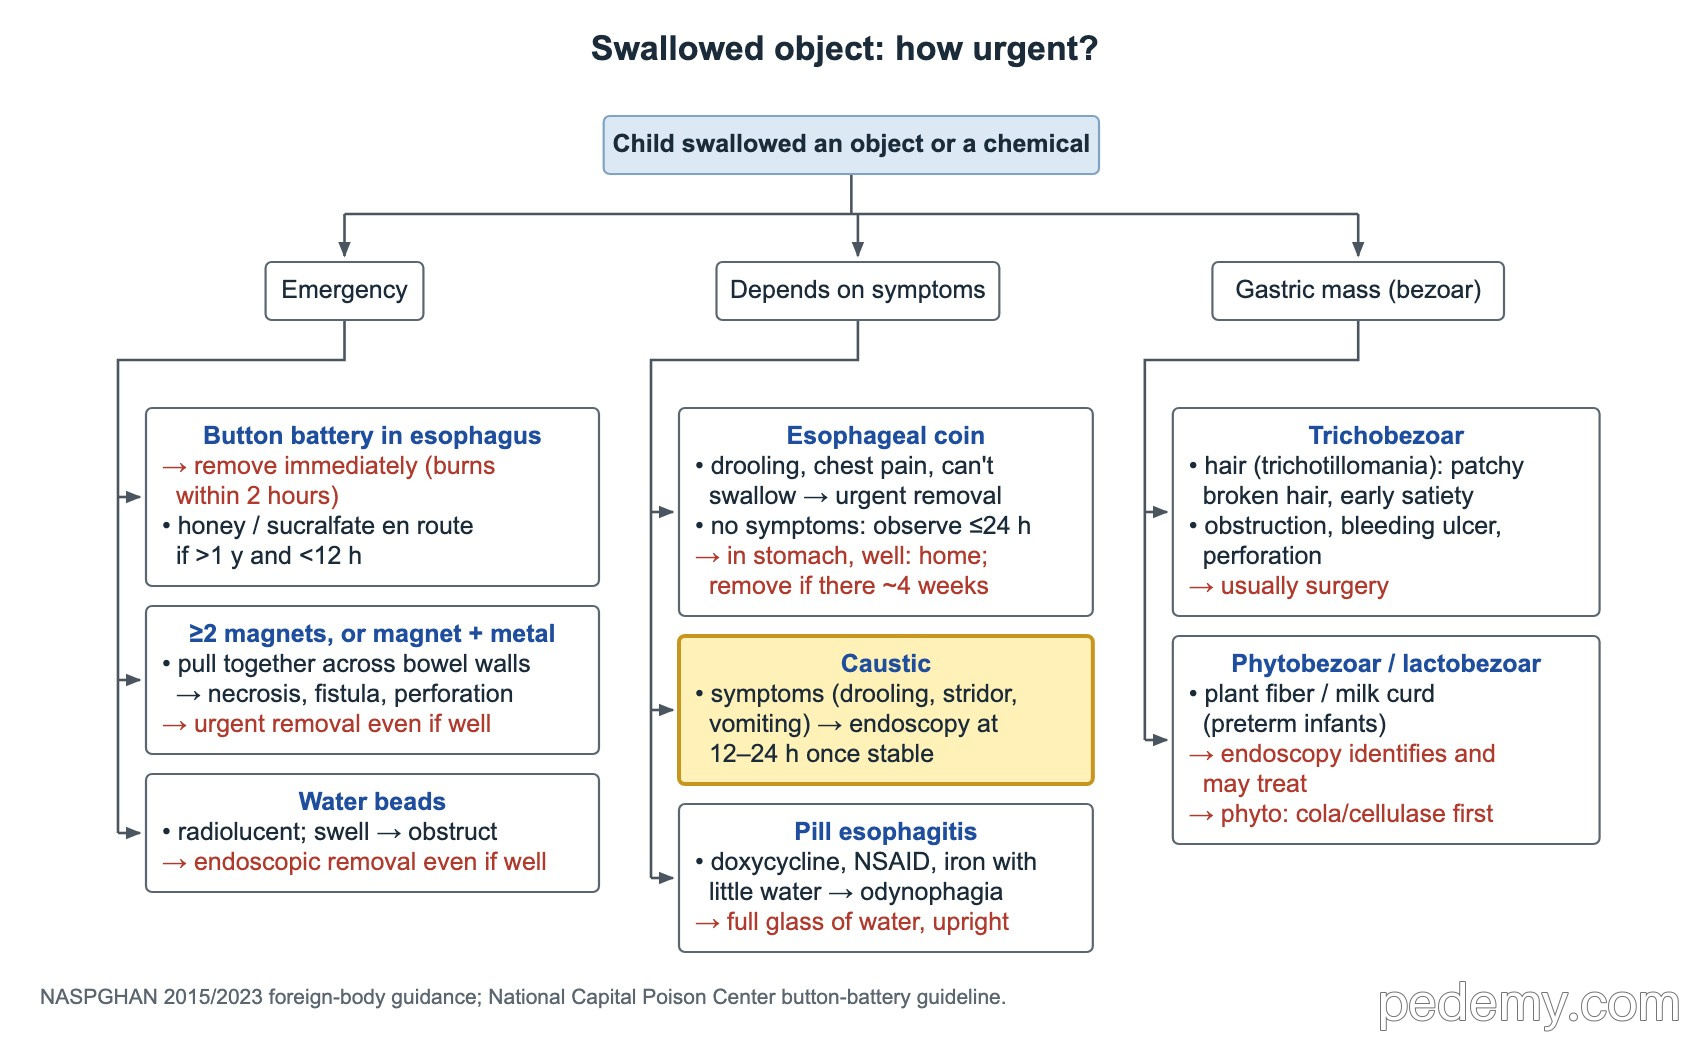
- Caustic ingestion with symptoms (drooling, stridor, vomiting): stabilize the airway, then plan upper endoscopy at 12–24 hours to grade the injury.
- No symptoms does not always mean no injury; decide on endoscopy with GI and poison control.
- Pill esophagitis: doxycycline, NSAIDs or iron taken with little water, often at bedtime, cause odynophagia and retrosternal pain.
- Prevent it with a full glass of water and staying upright after the dose.
Bezoars
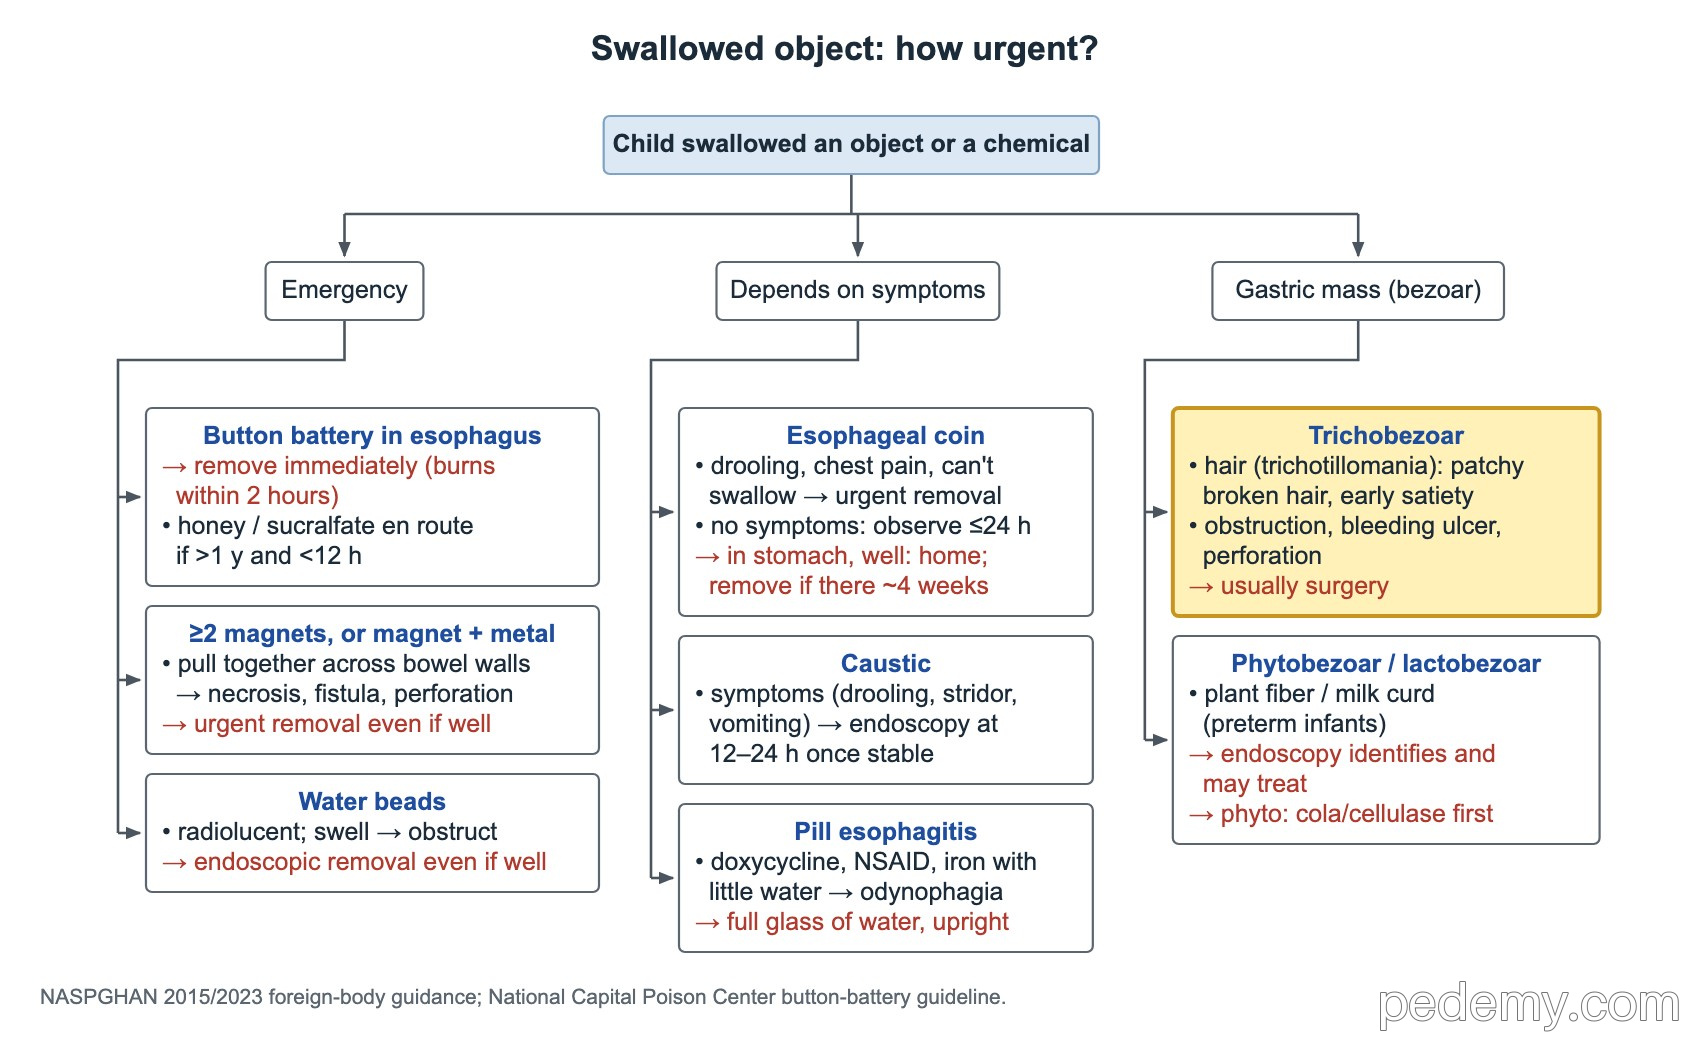
- Upper endoscopy shows the contents and can remove some bezoars.
- Risks: gastric outlet or bowel obstruction, mucosal ulceration with bleeding, perforation.
| Type | Made of / clue | Management |
|---|---|---|
| Trichobezoar | Hair; trichotillomania with patchy broken hair, early fullness, firm epigastric mass | Usually surgical removal (laparotomy) |
| Phytobezoar | Plant fiber | Dissolution first (cola, cellulase), then endoscopy |
| Lactobezoar | Milk curd in preterm infants on concentrated formula | Stop feeds, endoscopy if needed |
GERD in older children and teens
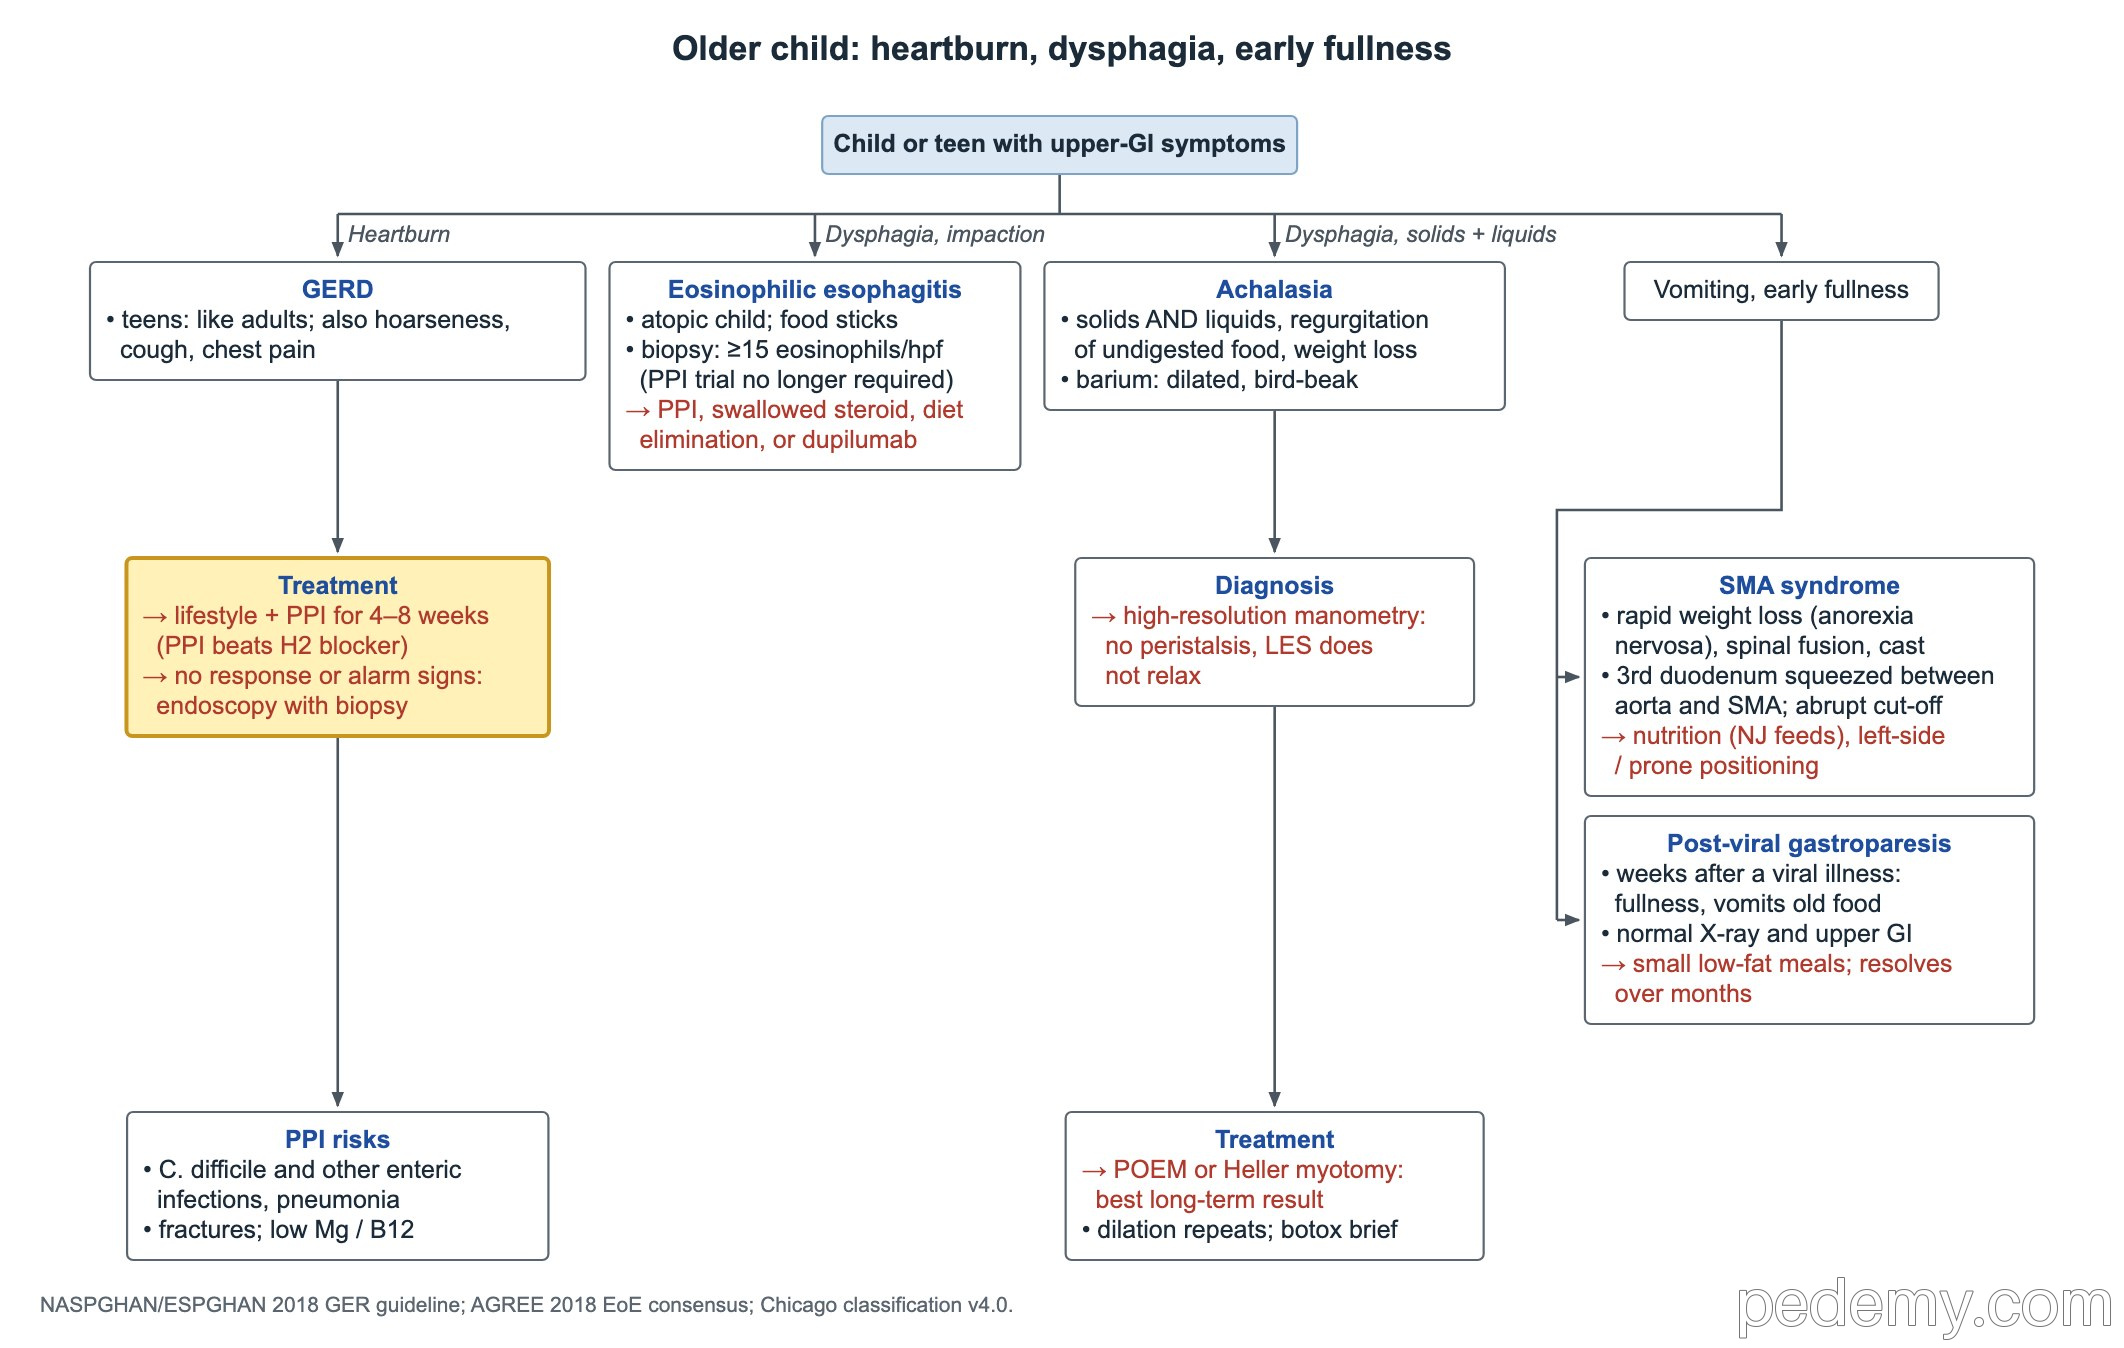
Teens with GERD describe heartburn and a sour taste, worse lying flat, like adults. They may also have hoarseness, cough or chest pain.
- Lifestyle changes plus a PPI for 4–8 weeks; PPIs heal esophagitis better than H2 blockers.
- No response after about 6 weeks, or alarm signs: upper endoscopy with biopsy.
- Long-term PPI risks: C. difficile and other enteric infections, pneumonia, fractures, low magnesium and B12.
- Weeks of fullness and vomiting of undigested food after a viral illness with a normal X-ray and upper GI suggest post-viral gastroparesis: small low-fat meals; it resolves over months.
- Rapid weight loss, spinal fusion or a body cast with bilious vomiting and early fullness suggests superior mesenteric artery syndrome.
Eosinophilic esophagitis and achalasia
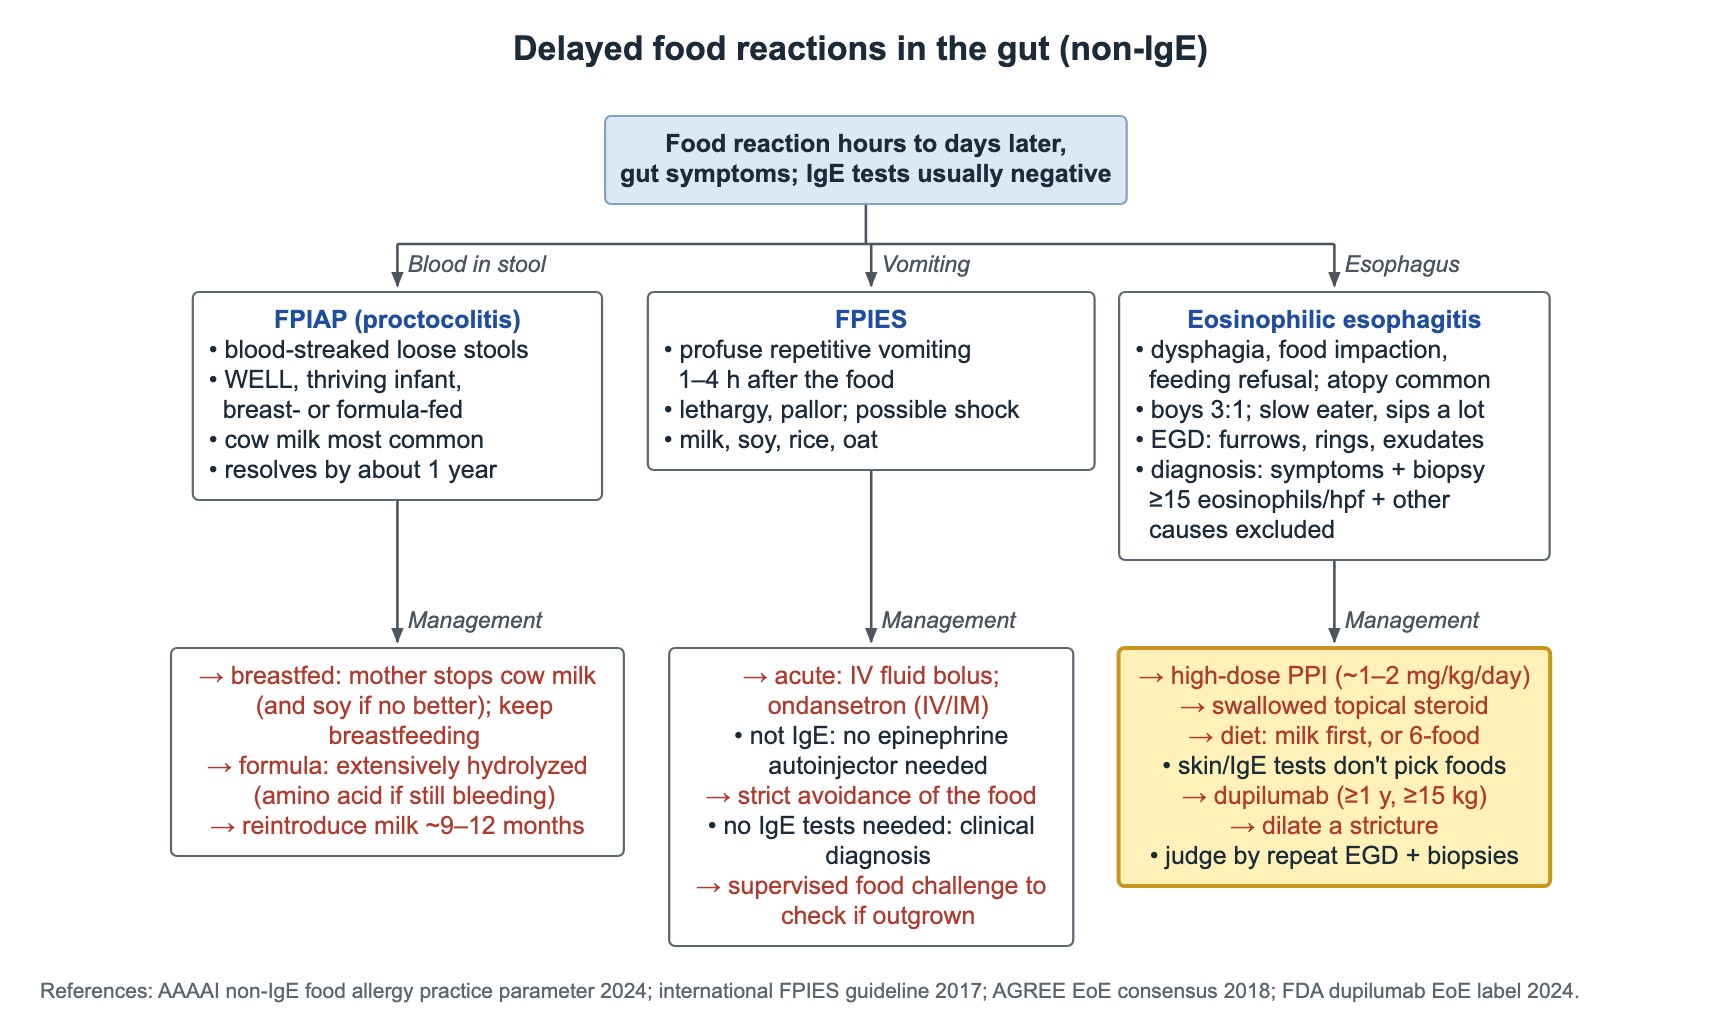
Eosinophilic esophagitis (EoE) is a chronic non-IgE, Th2-driven allergic inflammation. It is the most common cause of solid-food dysphagia and food impaction in teens. Boys outnumber girls about 3:1, and most have other atopy. Infants and toddlers present with feeding refusal, vomiting and poor growth; school-age children eat slowly, chew a long time and drink with every bite.
Diagnosis: symptoms plus esophageal biopsy with ≥15 eosinophils per high-power field, after other causes are excluded. A PPI trial is no longer required first. Endoscopy shows linear furrows, rings, white exudates and strictures.
- High-dose PPI, about 1–2 mg/kg/day divided twice daily.
- Swallowed topical steroid: fluticasone puffs swallowed or budesonide slurry.
- Diet: remove cow milk first (the most common trigger), or a six-food elimination (milk, wheat, egg, soy, nuts, fish/shellfish). Skin-prick and IgE tests do not pick the foods.
- Dupilumab (IL-4/IL-13 blocker) is approved from age 1 year and 15 kg.
- Fibrotic stricture: endoscopic balloon dilation. Response is judged by repeat endoscopy with biopsies.
- Achalasia: dysphagia to solids and liquids, regurgitation of undigested food, weight loss; barium shows a dilated esophagus with a bird-beak. High-resolution manometry confirms it (absent peristalsis, the LES does not relax). POEM or laparoscopic Heller myotomy gives the best long-term result; dilation often needs repeating and botulinum toxin is brief.
Common questions
What should you do if a child swallows a button battery?
Go to the emergency department at once. A battery in the esophagus is removed immediately. If the child is over 1 year and it was swallowed within 12 hours, honey can be given on the way.
Can a swallowed coin pass on its own?
Often. A child with no symptoms and a coin in the esophagus can be watched for up to 24 hours with a repeat X-ray; a coin in the stomach usually passes.
How is eosinophilic esophagitis diagnosed?
By upper endoscopy with biopsies showing at least 15 eosinophils per high-power field, in a child with esophageal symptoms and no other cause.
Study this topic
Sources
- NASPGHAN 2015: Management of ingested foreign bodies in children (JPGN)
- ESPGHAN 2021: Button battery ingestion in childhood (JPGN)
- AGA/JTF 2020: Clinical guidelines for eosinophilic esophagitis (Gastroenterology)
- NASPGHAN/ESPGHAN 2018: Pediatric gastroesophageal reflux guidelines (JPGN)
Written for Pedemy in our own words from the sources above; checked November 2026. For education only, not medical advice; check doses and local protocols before treating a patient. Pedemy is independent and not affiliated with or endorsed by the organizations cited.